Often, yes. A stroke or a TIA does not automatically disqualify you from life insurance in South Dakota, and the diagnosis by itself usually is not what decides the outcome. What actually moves the needle, according to two national carriers’ own 2025-2026 underwriting guides, is the type of event, how long ago it happened, what deficits remain, and what the rest of your medical file shows. This guide walks through how life insurance underwriting actually treats a stroke history in 2026, using real carrier documents and federal and state health data, so you can find out where you likely stand instead of assuming the answer is no.
The short version
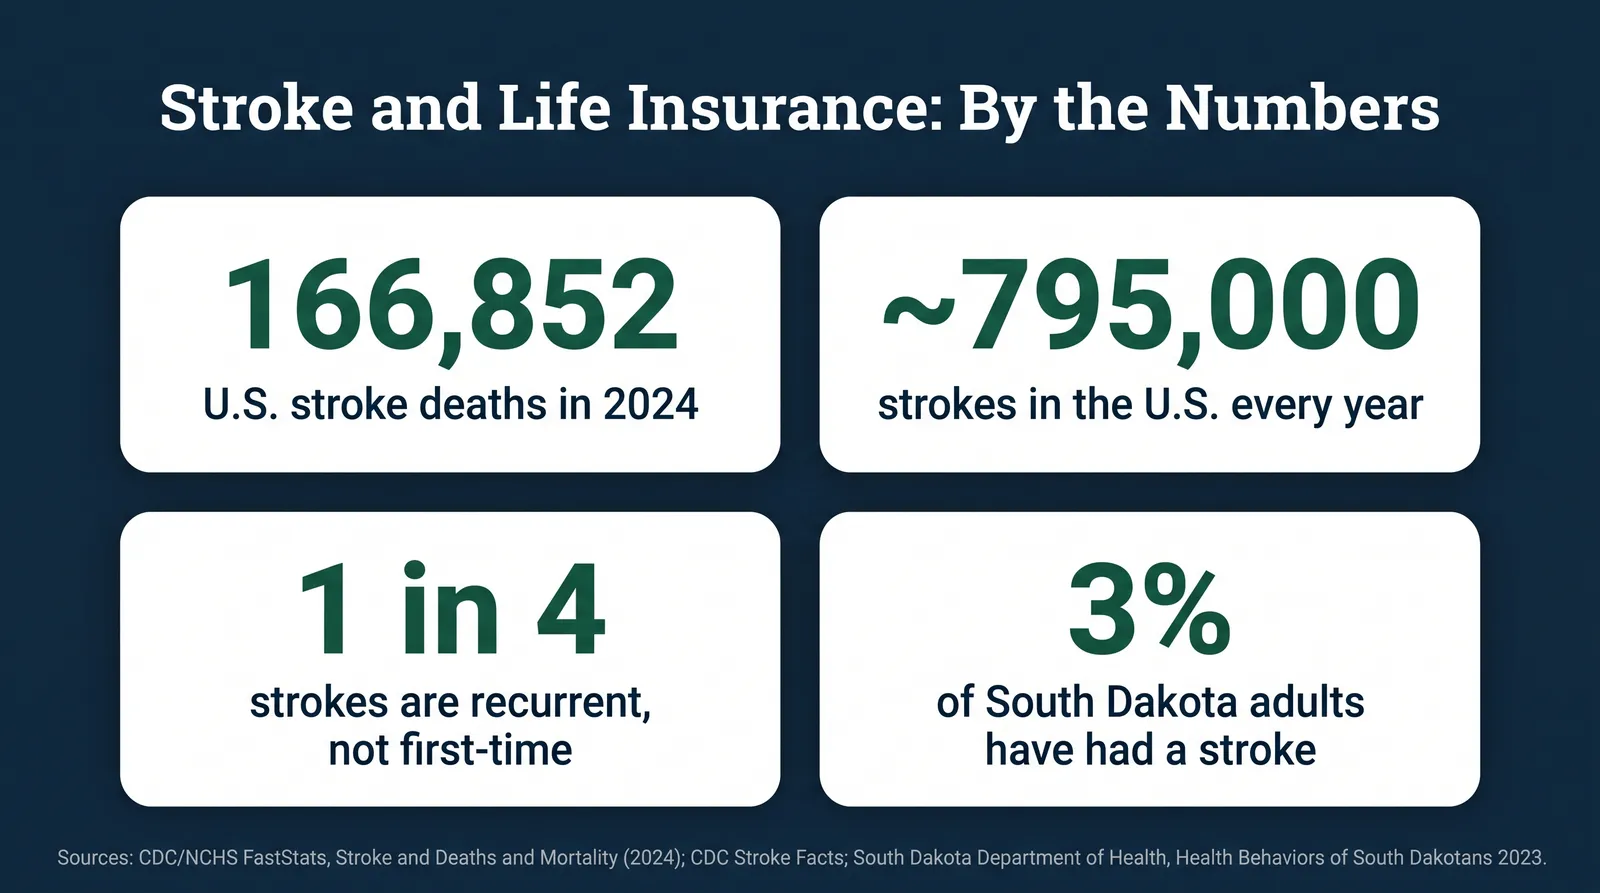
- Roughly 795,000 people have a stroke in the United States every year, and close to 1 in 4 of those are recurrent strokes, according to the CDC's Stroke Facts page — carriers underwrite this history constantly, not as a rare exception.
- Stroke was the 4th leading cause of death in the U.S. in 2024, with 166,852 deaths, per the CDC's National Center for Health Statistics.
- Both Banner Life family of companies and Pacific Life Insurance Company treat a stroke within the last 6 months as a decline-or-postpone trigger, which means the calculation changes once you are past that window, not that the history disqualifies you permanently.
- In South Dakota, 3% of adults, an estimated 23,000 people, reported ever having had a stroke as of 2023, according to the South Dakota Department of Health — the same rate as the national median that year.
- South Dakota law requires life insurance policies to become incontestable, except for fraud or nonpayment, two years after issue (SDCL 58-15-10) — a real legal protection for coverage you already hold, separate from how a new application gets underwritten.
Why “I probably can’t get covered now” is the wrong starting assumption
Here is the pain point in the words we hear most often: I had a stroke, or my doctor said it was a TIA, a mini-stroke, so I have just assumed life insurance is either off the table or not worth the trouble of applying and finding out. That assumption keeps people from ever starting the process, and it is not supported by how carriers actually underwrite stroke history in 2026.
Underwriting, for anyone new to the term, is the process a life insurance company uses to evaluate an applicant’s risk and decide whether to offer coverage, at what price, and in which risk class, also called a rate class, a tier like Preferred Plus, Preferred, Standard Plus, or Standard that sets your premium relative to the carrier’s base rate. A table rating, written as Table 1 through Table 12 or Table A through Table J depending on the carrier, is a priced step above Standard for higher-risk applicants; each step adds a set percentage to the premium, with the exact percentage set by the individual carrier. An Attending Physician Statement (APS) is a request for your medical records from a doctor, neurologist, or hospital, used when an underwriter needs more detail than the application alone provides; it is required in nearly every stroke case at both carriers reviewed here. A contestability period is the window, commonly two years, during which an insurer can investigate and potentially deny a claim if the application contained a material misstatement.

None of this is secret information. Life insurance carriers publish underwriting guides for their agents that lay out, in table form, what best-case and worst-case outcomes look like for dozens of health conditions, stroke included. We pulled the current guides from two national carriers, Banner Life family of companies (Banner Life Insurance Company and William Penn Life Insurance Company of New York) and Pacific Life Insurance Company, to show what those guides actually say about a stroke or TIA history, in plain terms, with no guesswork.
How common is stroke, really?
Before getting into underwriting mechanics, it is worth establishing the scale of what we are talking about, because a lot of the fear behind this pain point comes from treating a stroke as rare or unusual. It is not. Stroke has been one of the leading causes of death in the United States for decades, and the numbers behind that fact are large enough that carriers have built specific, published underwriting rules for it, the same way they have for heart disease or diabetes.
Someone in the United States has a stroke every 40 seconds, and someone dies of one roughly every 3 minutes and 14 seconds, according to the CDC’s Stroke Facts page. About 87% of all strokes are ischemic, meaning blood flow to the brain is blocked, typically by a clot; the remainder are hemorrhagic, caused by bleeding in or around the brain, which the same page notes tend to be evaluated more cautiously because of their higher severity. Of the roughly 795,000 strokes that happen in the U.S. each year, about 610,000 are a person’s first stroke, and about 185,000, nearly 1 in 4, happen in someone who has already had one. That recurrence rate is exactly why both carrier guides reviewed here single out “multiple strokes” as its own, more serious category, separate from a single, resolved event.
| Measure | Figure | Period |
|---|---|---|
| U.S. deaths from stroke, cause-of-death rank 4 | 166,852 | 2024 |
| Stroke death rate per 100,000 population | 49.1 | 2024 |
| Strokes per year in the U.S. (about 610,000 first-time) | ~795,000 | 2026 report |
| Recurrent strokes per year (in someone with a prior stroke) | ~185,000 (~1 in 4) | 2026 report |
| U.S. adults who report ever having had a stroke | 7.8 million (3.1%) | 2018 survey |
| South Dakota adults who report ever having had a stroke | 3% (about 23,000 people) | 2023 |
| National median, same measure | 3% | 2023 |
Sources: CDC, Stroke Facts (accessed September 2026); CDC/National Center for Health Statistics, FastStats — Stroke, citing National Vital Statistics System mortality data (2024) and Summary Health Statistics Tables for U.S. Adults, National Health Interview Survey (2018); South Dakota Department of Health, The Health Behaviors of South Dakotans 2023 (published September 2025), South Dakota Behavioral Risk Factor Surveillance System.
These figures measure different things, from different years
The 7.8 million / 3.1% national figure comes from a 2018 federal health survey, the most recent period that specific CDC FastStats table cites; it is not directly comparable to South Dakota's 2023 state survey figure, even though both land at roughly 3%. Neither number is a life insurance approval rate. They are included to show scale, not to predict any individual's underwriting outcome.
Leading causes of death in the United States, 2024
Source: CDC/National Center for Health Statistics, FastStats — Deaths and Mortality, Mortality in the United States, 2024, data table for figure 4. Accessed September 2026.
Stroke also is not a young person’s disease exclusively, but it is not exclusively an old person’s disease either. The CDC notes that in 2014, 38% of people hospitalized for stroke were under age 65, which is part of why this guide does not assume every reader worried about this is retired. Whatever your age, the same underwriting mechanics apply, and the same two guides below spell out how.
What underwriters actually look at, in their own published guides
This is the mechanism behind the pain point: most people picture underwriting as a single yes/no checkbox next to “stroke.” That is not how it works. Both carrier guides we reviewed break the question into a specific event type, a specific timeline, and specific documentation, not a blanket rule.
Pacific Life’s Underwriting Guide (PLF4249-01, November 2025) groups “Stroke, Cerebrovascular Accident (CVA), Cerebrovascular Disease (CVD), Transient Ischemic Attack or mini-stroke (TIA)” together under one impairment category. It requires an Attending Physician Statement for all cases and states that outcomes “vary by severity, age of onset, and time since occurrence,” with the explicit note that the event “must be greater than 6 months to consider,” and that multiple strokes are a decline. Separately, in Pacific Life’s Uninsurable Conditions and Conditions by Timeline table, a stroke (CVA) “within 6 months” is listed among the issues an application should not be submitted for, alongside conditions like a heart attack within 6 months or a bypass within 3 months.
Banner Life’s Field Guide for Life Insurance Underwriting (March 2026), under its “Declines and postpones” section, lists Stroke (CVA) with three specific triggers: the carrier “may not be able to offer if within 6 months (dependent on type),” a severe case involving “impaired cognition, wheelchair or needing assistance with ADLs” (activities of daily living, the basic self-care tasks like bathing, dressing, and eating), or a history of multiple strokes. Separately, Banner Life’s APS ordering guidelines list “Cerebral Vascular Disease (Hemorrhage/Stroke/TIA)” as a condition that will typically require an Attending Physician Statement at all ages and amounts, alongside conditions like heart disease, diabetes, and cancer.
| Scenario | Banner Life family of companies | Pacific Life |
|---|---|---|
| TIA, resolved, event more than 6 months ago | Outside the decline-or-postpone window; individual consideration; APS required | Grouped with stroke/CVA/CVD; APS required for all cases; individual consideration once past 6 months |
| Ischemic stroke, mild, no residual deficits, more than 6 months ago | Not on the decline list outside the recent-event window; individual consideration | Outcome depends on severity, age of onset, and time since occurrence |
| Stroke within the last 3 months | Within the 6-month decline-or-postpone window; likely decline or postpone | Inside the "must be greater than 6 months" uninsurable window; do not submit |
| Severe stroke with lasting cognitive impairment or need for assistance with daily activities | Listed as a specific decline trigger regardless of time since event | Not separately listed at this severity level in this guide; evaluated case by case |
| More than one stroke on record | Listed as a decline trigger | Listed as a decline ("decline for multiple") |
| Hemorrhagic stroke | Not separately broken out from stroke (CVA) in this guide's decline list | Grouped under the same CVA/CVD category; evaluated on severity and time since event |
Sources: Banner Life family of companies (Banner Life Insurance Company and William Penn Life Insurance Company of New York), Field Guide for Life Insurance Underwriting, March 2026; Pacific Life Insurance Company, Underwriting Guide: Confidence for Generations (PLF4249-01), November 2025. Both guides state that individual underwriting decisions depend on the full case and may differ from these best-case scenarios. Every carrier sets its own guidelines; these two are shown as examples, not the full market.
Two things stand out from putting these side by side. First, both carriers converge on roughly the same floor: a stroke within the last 6 months is what actually triggers a decline or a “do not submit yet” flag, not the diagnosis itself, and both require medical records in essentially every case rather than taking the applicant’s word for it. Second, the two guides do not handle every scenario identically, especially how they weigh severity and lasting deficits versus a clean recovery, which is exactly why shopping matters when a stroke history is part of the picture. A file that gets a cautious answer from one carrier can get a meaningfully different one from another, because each company sets its own underwriting philosophy and risk appetite.
These are illustrative examples, not a promise
The table above reflects two carriers' published guidelines as of the dates shown, describing example outcomes under specific, stated conditions. Underwriting decisions are made case by case, guidelines change, and other carriers set their own rules that may differ from either example here. Nothing here is a quote, an approval, or a guarantee for any individual applicant.

TIA, ischemic stroke, hemorrhagic stroke: why the type matters
Part of why this pain point sticks is that “stroke” gets used as one word for several genuinely different medical events, and underwriters do not treat them as interchangeable.
A transient ischemic attack (TIA), sometimes called a mini-stroke, produces the same warning signs as a stroke, sudden numbness, weakness, or trouble speaking, but the symptoms resolve on their own, typically within minutes to hours and by definition within 24 hours, without the permanent brain tissue damage a completed stroke leaves behind. An ischemic stroke, the most common type at about 87% of all strokes per the CDC’s Stroke Facts page, happens when a clot blocks blood flow to part of the brain. A hemorrhagic stroke happens when a blood vessel in or near the brain ruptures and bleeds; it is less common but generally carries a higher immediate severity, which is part of why Pacific Life’s guide groups it under the same cautious, individual-consideration category as stroke and CVD rather than giving it a separate, more lenient path.
Both guides reviewed here fold TIA into the same impairment category as stroke rather than treating it as automatically minor. That surprises some applicants who assume a TIA, because the symptoms went away, will not even come up. In practice it does, because the underlying cause of a TIA, often the same narrowed or clot-prone blood vessels that cause a full stroke, is exactly what an underwriter wants documented: what the imaging showed, what workup was done to find the cause, and what treatment followed. A TIA with a clear cause that was identified and treated, and with normal follow-up imaging, tends to underwrite more favorably than a completed stroke with ongoing deficits, but “TIA” alone is not a pass.
A worked, hypothetical example
Take a hypothetical, illustrative case: a 58-year-old South Dakota resident had an ischemic stroke 14 months ago, was hospitalized for four days, received clot-dissolving treatment, and has since fully regained speech and motor function with no residual weakness. A follow-up MRI eight months after the event showed no new changes, blood pressure has been well-controlled on medication since, and the person has not smoked in over fifteen years. Cardiology and neurology follow-up visits have been routine, with the most recent one three months ago showing a stable, well-managed picture.
Under Pacific Life’s published guide, this case is well past the “must be greater than 6 months” threshold in the Uninsurable Conditions table, moving it into the Medical Risks category where the guide states the outcome “varies by severity, age of onset, and time since occurrence”; an Attending Physician Statement would be ordered as it is for every stroke case. Under Banner Life’s guide, the same file is outside the 6-month decline-or-postpone window and does not show the severe markers (impaired cognition, wheelchair use, or ADL assistance) the guide lists as automatic decline triggers, which moves it into individual consideration rather than a fixed no. This is a hypothetical example built to show how the mechanics work, not a benefit estimate or approval for any real applicant; every case is evaluated on its own facts, its own imaging, and its own follow-up records.
Compare that to the version of this story that keeps people from ever applying: I had a stroke, so there’s no point asking, they’ll just say no. Based on what these two carriers actually publish, that assumption is very likely wrong for a stable, well-documented case like the one above, more than a year past the event with full recovery.
Assuming a stroke means "no" before applying
- Treats any stroke or TIA diagnosis as automatically disqualifying, no matter how long ago it happened or how well the recovery went
- Never checks what a specific, current carrier's guidelines actually say about the timeline, severity, and follow-up records in the file
- Either skips applying for coverage entirely, or applies once, gets a cautious answer, and treats it as final
Common outcomeCoverage never gets sized or bought, based on an assumption that was never checked
Laying out the specifics and comparing carriers
- Gathers the event date, type (TIA, ischemic, or hemorrhagic), imaging results, deficits, and follow-up care up front
- Compares how more than one carrier's guidelines treat that specific history, since the guides above show real differences
- Applies with a carrier whose published criteria and timeline actually fit the applicant's situation
Common outcomeAn actual underwriting decision, not a guess, and a comparison across carriers instead of one
What it costs to guess wrong
The real cost here is not a specific premium figure, since no honest source can quote you one without underwriting your actual file. It is what happens when the assumption of “I’ll be declined” goes unchecked, at a scale that is easy to underestimate. About 795,000 people have a stroke in the U.S. every year and close to 1 in 4 of those are recurrent, according to the CDC’s Stroke Facts page, and stroke-related costs in the U.S., including health care services, medications, and missed work, came to nearly $56.2 billion between 2019 and 2020 per the same source. This is not a small population making the same assumption. Two outcomes tend to follow, and both are avoidable:
- Going without coverage entirely, because applying feels pointless. If something happens to that person, the mortgage, the income replacement, the final expenses, none of it gets covered, not because they were actually uninsurable, but because they never found out.
- Applying with only one carrier, usually whichever company a search result or an ad surfaced first, and treating whatever answer comes back as the final word on “am I insurable,” when a different carrier’s published guidelines, as the comparison table above shows, might land somewhere else entirely, especially around severity and residual deficits.
Both trace back to the same root problem: treating an assumption as a fact instead of checking it against what carriers actually publish. Add to that the confusion between stroke, TIA, and the general category of “cardiovascular history,” and it is easy to see why so many people simply stop before they start.
Don't confuse this with no-exam or guaranteed-issue coverage
No-medical-exam and guaranteed-issue life insurance are real product categories that exist for people whose health history makes traditional underwriting harder. They are worth knowing about as a category. But jumping straight to one of those, without first checking what a fully underwritten policy's actual outcome would be for a specific, well-documented stroke history, can mean paying for a smaller amount of coverage than a person may have qualified for through the standard process. Compare both paths before assuming you need the second one.
How to work through this yourself before you apply
Here is the method, laid out step by step, no gatekeeping:
- Write down the specifics of your history. The exact type of event (TIA, ischemic stroke, or hemorrhagic stroke), the date, where it was treated, whether clot-dissolving treatment or a procedure was performed, what your imaging (CT or MRI) showed, and what caused it if that was identified (a clot, narrowed carotid artery, atrial fibrillation, or another source).
- Note your timeline against the 6-month window. Both carrier guides above treat roughly 6 months since the event as the earliest point an application is realistically considered rather than declined or postponed outright. An event from over a year ago with a clean follow-up MRI reads very differently to an underwriter than one from eight weeks ago.
- Document your recovery in specific terms. Not “I’m doing fine,” but what deficits, if any, remain; whether you need assistance with daily activities; your current medications for blood pressure, cholesterol, or blood thinning; and the date and findings of your most recent neurology or cardiology follow-up.
- Understand what actually triggers a decline versus individual consideration. Based on the two guides above, that is mainly: an event within roughly the last 6 months, severe lasting impairment such as needing assistance with daily activities, or a history of more than one stroke. Outside those specific triggers, a well-documented single event tends to move into individual, case-by-case underwriting rather than an automatic no.
- Answer every application question honestly and completely. South Dakota life insurance policies carry a contestability period, two years under SDCL 58-15-10, during which an insurer can investigate a claim and deny it for a material misstatement. Leaving something out to improve your odds up front creates real risk for your beneficiaries later.
- Compare more than one carrier before drawing a conclusion. The side-by-side table above shows two carriers can land in different places on the same scenario, particularly around severity and residual deficits. If one company’s answer does not feel right, that is not necessarily the final answer; it may just be that company’s particular risk appetite for your specific history.
How we help
We are an independent agency, which means we are not tied to one carrier’s risk appetite. When a stroke or TIA history is part of someone’s picture, that independence is exactly the point: instead of taking one company’s guidelines as the final word, we can look at how different carriers actually treat that specific history, timeline, and follow-up documentation, and compare the real options. We start with the specifics, the event type, the date, the recovery, the follow-up care, not a guess, and work from there. Compare My Options.
What you get
An actual underwriting answer instead of an assumption you never checked. A comparison across carriers instead of a single company’s guidelines standing in for “what’s possible.” And, if coverage makes sense once you have real numbers in front of you, a policy sized to your actual situation rather than whatever felt safest to guess at.
A stroke in your chart is not the same thing as a decline letter in your mailbox. The two carriers whose own guides we reviewed here would tell you the same thing: it depends on the timeline, the type, and the recovery, and most timelines do not end in "no" forever.
Mike MooreIf you would rather have someone local walk through your specific history with you, that is what we do. You can also run the timeline math yourself using the method above; most people find the carrier comparison is the part worth a second opinion once they have the specifics written down.
Related reading
If a different health condition is the concern, see our guides on life insurance with heart disease, life insurance with high blood pressure, life insurance with diabetes, and life insurance after cancer. If you are specifically weighing the exam-free path, see underwritten vs. no-exam life insurance and how no-medical-exam life insurance actually works.
Not sure this is the only condition in your file?
Weighing the no-exam route?
Read about no-medical-exam life insurance as a category before deciding.
Not ready to talk to anyone yet?
Read how it works first and come back when you are, or reach us through our contact page when you have questions.
Frequently asked questions
Can you get life insurance after a stroke or TIA?
Often, yes, once enough time has passed and the specifics are documented. Two national carriers’ own 2025-2026 underwriting guides treat a stroke as a condition to evaluate on its facts, not an automatic decline. Pacific Life’s guide states outcomes “vary by severity, age of onset, and time since occurrence,” and both Pacific Life and Banner Life list a stroke within the last 6 months as a trigger that can result in a decline or postponement. Past that window, the file moves into individual, case-by-case consideration rather than a fixed no.
How long after a stroke can you apply for life insurance?
There is no single industry-wide waiting period, and a specific number quoted without a named source should be treated with skepticism. What is actually documented: Pacific Life’s Uninsurable Conditions table (PLF4249-01, November 2025) lists stroke (CVA) as a condition that “must be greater than 6 months” from the event even to be considered, and Banner Life’s Field Guide (March 2026) lists stroke within 6 months, dependent on type, as a possible decline. Both guides converge on 6 months as the earliest realistic point to apply, not a guarantee of approval at that point.
What’s the difference between a stroke and a TIA for underwriting purposes?
A transient ischemic attack, or TIA, produces stroke-like symptoms that resolve, typically within 24 hours, without the permanent tissue damage a completed stroke causes; it is often called a mini-stroke. Pacific Life’s guide groups stroke, cerebrovascular disease, and TIA under one impairment category with the same requirement, an Attending Physician Statement in all cases and a minimum of 6 months since the event. In practice, a well-documented TIA with a clear, treated cause tends to underwrite more favorably than a completed stroke with residual deficits, but neither guide treats a TIA as automatically minor.
What is a table rating, and how would it apply after a stroke?
A table rating is a priced step above a carrier’s standard rate class, used when an applicant’s combined risk factors are elevated but not high enough to decline. It is not a decline. Both carrier guides describe stroke and TIA history as needing individual consideration rather than one fixed rating, which means the actual outcome for a given file depends on specifics: how long ago the event happened, what type it was, what deficits remain, and what the rest of the medical record shows.
Will a decline at one insurance company follow you to another?
Not automatically, and South Dakota law does not require it to. SDCL 58-33-26 prohibits an insurer from unfairly discriminating between insureds with genuinely similar risk characteristics, but it does not require every carrier to apply identical underwriting thresholds. Because guidelines differ by company, as the Banner Life and Pacific Life comparison in this guide shows, an unfavorable outcome at one carrier reflects that carrier’s specific rules applied to your file, not a verdict on your insurability everywhere.
Does a stroke history ever stop mattering for a policy you already own?
For a policy you already own and have paid premiums on, yes, in a specific legal sense. SDCL 58-15-10 requires South Dakota life insurance policies to become incontestable, except for fraud or nonpayment of premium, after the policy has been in force for two years from its issue date. Once a policy passes its second anniversary, the insurer generally cannot rescind it over an application misstatement discovered later. That protection covers coverage you already hold; a new application is a separate process with its own underwriting at each carrier.
How common is stroke, really, and how common is having a second one?
Common enough that carriers underwrite it constantly, not as an edge case. Roughly 795,000 people have a stroke in the United States every year, and about 185,000 of those, close to 1 in 4, are recurrent strokes in someone who has already had one, according to the CDC’s Stroke Facts page. Stroke was the 4th leading cause of death in the U.S. in 2024, with 166,852 deaths, per the CDC’s National Center for Health Statistics. In South Dakota, 3% of adults, an estimated 23,000 people, reported ever having had a stroke as of 2023, according to the South Dakota Department of Health, the same as the national median that year.
What should I actually do if I’m worried a stroke will get me declined?
Gather the specifics before you apply: the exact date of the event, whether it was a TIA, ischemic stroke, or hemorrhagic stroke, what the imaging and workup showed, any deficits and how much they have resolved, your current medications, and your follow-up neurology or cardiology care. Then compare how more than one carrier’s published guidelines treat that specific history, since the two guides in this article show real differences in emphasis, rather than assuming one company’s rules or one past experience settles the question everywhere.
Sources
- CDC — Stroke Facts — every 40 seconds someone has a stroke, every 3 minutes 14 seconds someone dies of one; about 795,000 strokes per year (about 610,000 first-time, about 185,000 recurrent, nearly 1 in 4); about 87% of strokes are ischemic; stroke-related costs nearly $56.2 billion, 2019-2020; 38% of stroke hospitalizations were under age 65 (2014 data); symptom awareness 93% recognized sudden numbness, only 38% knew all major symptoms; accessed September 2026
- CDC/National Center for Health Statistics — FastStats: Stroke — 166,852 U.S. stroke deaths (2024), rate 49.1 per 100,000, cause-of-death rank 4, source National Vital Statistics System via CDC WONDER; 7.8 million U.S. adults (3.1%) report ever having had a stroke, source Summary Health Statistics Tables for U.S. Adults, National Health Interview Survey 2018; accessed September 2026
- CDC/National Center for Health Statistics — FastStats: Deaths and Mortality — 2024 leading causes of death: heart disease 683,491, cancer 619,876, accidents 197,449, stroke 166,852; source Mortality in the United States, 2024, data table for figure 4; accessed September 2026
- South Dakota Department of Health — The Health Behaviors of South Dakotans 2023 — South Dakota Behavioral Risk Factor Surveillance System report, published September 2025; Table 1, “Ever Had a Stroke”: 3% of South Dakota adults, estimated 23,000 people, 2023; national median 3%, 2023; accessed September 2026
- Banner Life family of companies — Field Guide for Life Insurance Underwriting — March 2026 edition; Stroke (CVA) decline/postpone triggers (within 6 months dependent on type, severe cases with impaired cognition or need for ADL assistance, multiple strokes); Cerebral Vascular Disease (Hemorrhage/Stroke/TIA) APS requirement; accessed September 2026
- Pacific Life Insurance Company — Underwriting Guide: Confidence for Generations (PLF4249-01) — November 2025 edition; Uninsurable Conditions/Conditions by Timeline table (Stroke (CVA): must be greater than 6 months); Medical Risks table (Stroke/CVA/CVD/TIA: APS required for all cases, varies by severity/age of onset/time since occurrence, decline for multiple); accessed September 2026
- South Dakota Legislature — SDCL 58-15-10, Incontestability provision required — two-year incontestability period for South Dakota life insurance policies, except fraud or nonpayment of premium; accessed September 2026
- South Dakota Legislature — SDCL 58-33-26, Unfair discrimination as to terms and conditions of insurance — prohibits unfair discrimination between insureds with like risk characteristics; accessed September 2026
Related reading: life insurance with heart disease, life insurance with high blood pressure, life insurance with diabetes, life insurance after cancer, underwritten vs. no-exam life insurance, and no-medical-exam life insurance in South Dakota.
Before you act on any of this
This article is general education, not insurance, legal, financial, medical, or tax advice, and it is not an underwriting decision or a promise of coverage for any individual. Carrier guidelines shown here are illustrative examples current as of the dates listed and are subject to change; other carriers set different rules. Product availability, features, and rates vary by carrier and are subject to underwriting. No coverage exists until a policy is issued and in force. Any guarantees are subject to the claims-paying ability of the issuing insurer. Please review actual policy documents and speak with a licensed agent about your own situation.
The timeline and the type matter more than the word “stroke”
Most people who assume a stroke closes the door on life insurance have never actually checked, because the fear of a “no” feels worse than not asking. What two carriers’ own published underwriting guides show is a lot more specific, and a lot less bleak, than that fear: the type of event, how long ago it happened, your recovery, and your follow-up records, not the word “stroke” by itself. You can write down your own specifics this week, the event type, the date, the imaging results, the follow-up care, and see how they line up against the timelines above. That comparison is worth more than another year of guessing.
Want an actual answer instead of a guess?
We'll walk through your specific stroke or TIA history and compare carrier options sized to what's actually in your file, not an assumption about it.