No, a mental health history does not automatically disqualify you from life insurance, and it usually doesn’t push you into the most expensive tier either. Underwriting field guides published by two national carriers in late 2025 and early 2026 show that mild, well-controlled anxiety and a single resolved episode of depression can qualify for a carrier’s best or near-best rate classes. What actually moves the outcome is severity, how long you’ve been stable, the type of treatment, and whether there’s a hospitalization or self-harm history involved, not the fact that a diagnosis exists on your chart. This guide walks through what carriers actually look at, using their own published underwriting criteria, what a mental health history statistically covers in South Dakota and nationally, and the specific steps to find your real answer instead of guessing at one.
The short version
- Mild anxiety well controlled on a single medication can qualify for a carrier's top non-tobacco rate class, and a single depressive episode lasting less than a year with no current medication can also reach the top tier, according to Banner Life family of companies' Field Guide for Life Insurance Underwriting (March 2026).
- What actually triggers a decline or a postponed decision, per two carriers' published guides, is narrower than most people assume: a bipolar diagnosis within the last year, a suicide attempt within the last one to two years, current hospitalization, or a treatment change within the last six months.
- An estimated 13.1% of Americans age 12 and older had depression in a given two-week period between August 2021 and August 2023, up from 8.2% in 2013-2014, according to the CDC's National Center for Health Statistics.
- In South Dakota, 18.2% of adults reported ever being diagnosed with a depressive disorder as of 2024, according to an analysis of CDC Behavioral Risk Factor Surveillance System data by America's Health Rankings, a rate lower than the 22.0% national average.
- 11.4% of U.S. adults took prescription medication for depression in 2023, according to the CDC, and carrier guides treat medication use as one factor among several rather than an automatic disqualifier.
Why “I’ll probably get declined” is the wrong starting assumption
Here’s the pain point in the words we hear most often: I have anxiety, or I take an antidepressant, or I was hospitalized once years ago, so I’ve just assumed I either can’t get life insurance or it isn’t worth applying and finding out. That assumption keeps a lot of people from ever starting the process, and it isn’t supported by how carriers actually underwrite mental health history in 2026.
Underwriting, for anyone new to the term, is the process a life insurance company uses to evaluate an applicant’s risk and decide whether to offer coverage, at what price, and in which risk class (also called a rate class), a tier like Preferred Plus, Preferred, Standard Plus, or Standard that determines your premium relative to the carrier’s base rate. A table rating, sometimes written as Table 1 through Table 12 or Table A through Table J depending on the carrier, is a step above Standard used for higher-risk applicants; each step adds a set percentage to the premium, with the exact percentage set by the individual carrier. An Attending Physician Statement (APS) is a request for your medical records from a doctor or clinic, used when an underwriter needs more detail than the application alone provides.

None of that is secret information. Life insurance carriers publish field guides for their underwriters and agents that lay out, in table form, what best-case and worst-case outcomes look like for dozens of health conditions, mental health included. We pulled the current guides from two national carriers, Banner Life family of companies (Banner Life Insurance Company and William Penn Life Insurance Company of New York) and Pacific Life Insurance Company, to show what that actually says, plain terms, no guesswork.
How common is a mental health history, really?
Before getting into underwriting mechanics, it’s worth establishing the scale of what we’re talking about, because a lot of the fear behind this pain point comes from treating a mental health diagnosis as rare or unusual. It isn’t.
| Measure | Figure | Period |
|---|---|---|
| U.S. adolescents/adults 12+ with depression (2-week period) | 13.1% | Aug 2021 – Aug 2023 |
| Same measure, a decade earlier | 8.2% | 2013 – 2014 |
| U.S. adults with a major depressive episode in the past year | 8.3% (21.0 million) | 2021 |
| U.S. adults on prescription medication for depression | 11.4% | 2023 |
| South Dakota adults ever diagnosed with a depressive disorder | 18.2% | 2024 |
| U.S. adults ever diagnosed with a depressive disorder | 22.0% | 2024 |
Sources: CDC/NCHS Data Brief No. 527 (April 2025) and No. 528 (April 2025); National Institute of Mental Health (NIMH), Major Depression statistics; America's Health Rankings analysis of CDC Behavioral Risk Factor Surveillance System data. Accessed August 2026.
Depression prevalence: national point-in-time vs. lifetime, and South Dakota vs. national lifetime
These four figures measure different things (a two-week snapshot, a past-year episode, and a lifetime diagnosis) and aren't directly comparable to each other as a trend. Sources: CDC/NCHS Data Brief No. 527 (April 2025); NIMH Major Depression statistics (2021 data); America's Health Rankings analysis of CDC BRFSS data (2024). Accessed August 2026.
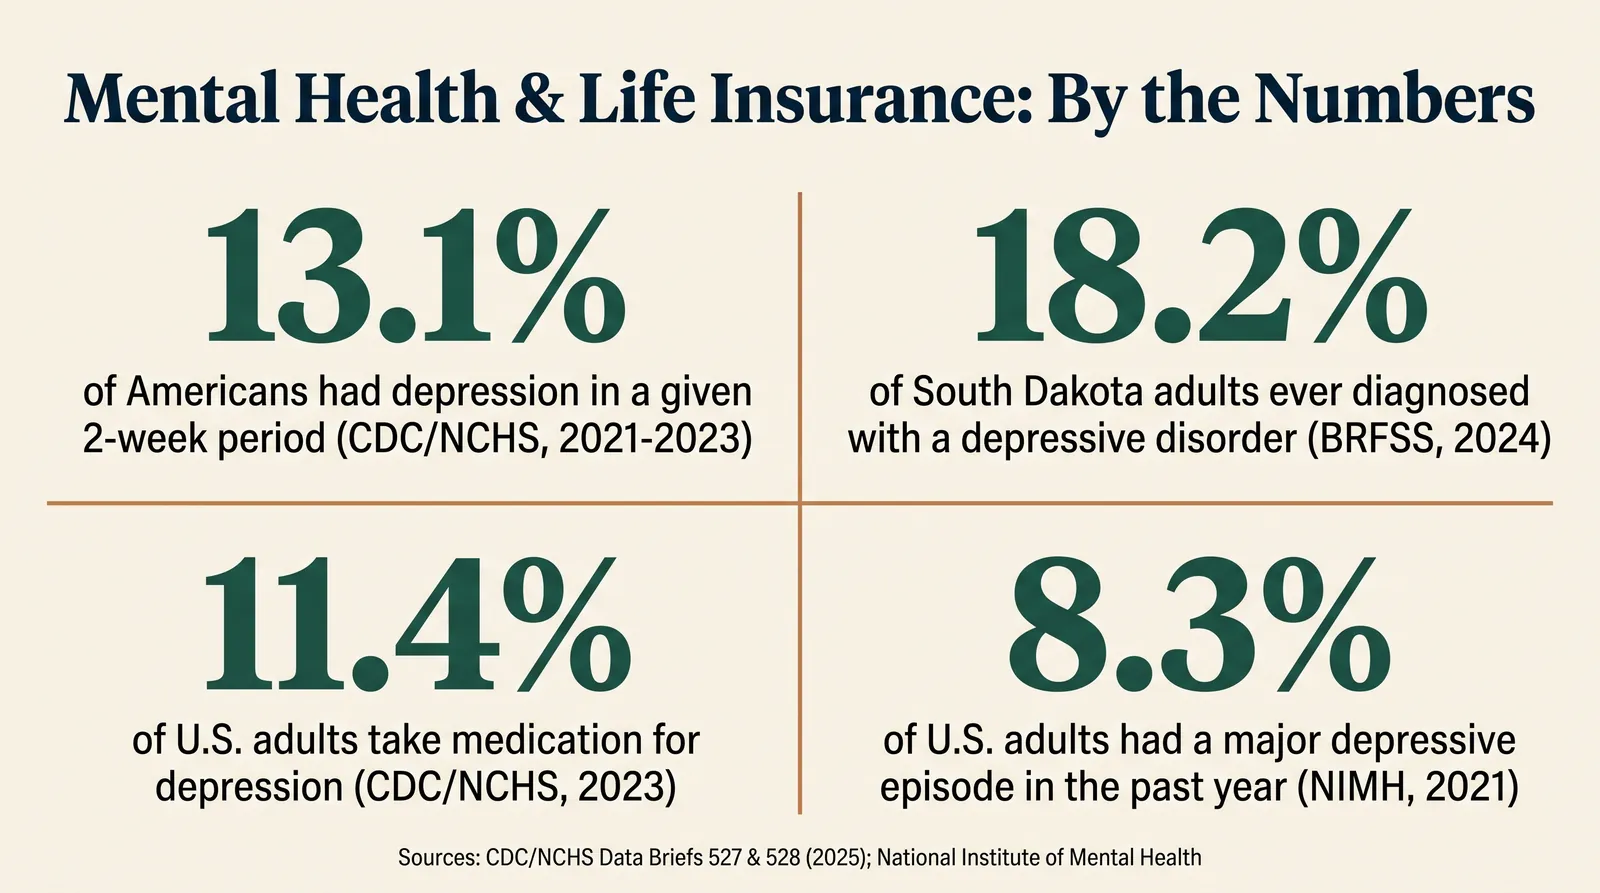
Put plainly: roughly 1 in 5 South Dakota adults has, at some point, been diagnosed with a depressive disorder, and that’s before counting anxiety, adjustment disorders, or other conditions that show up on the same underwriting questionnaires. Assuming a mental health history is a rare, disqualifying edge case gets the scale backwards. It’s common enough that carriers have built specific, published rules for it, the same way they have for blood pressure or cholesterol.
These figures measure different things
A two-week prevalence rate, a past-year episode rate, and a lifetime "ever diagnosed" rate answer different questions and will always produce different numbers from the same population. None of the figures above are a life insurance approval rate. They're included to show scale, not to predict any individual's underwriting outcome.
What underwriters actually look at, in their own published guides
This is the mechanism behind the pain point: most people picture underwriting as a single yes/no checkbox next to “mental health disorder.” That isn’t how it works. Both carrier guides we reviewed break the question into a small set of specific factors.
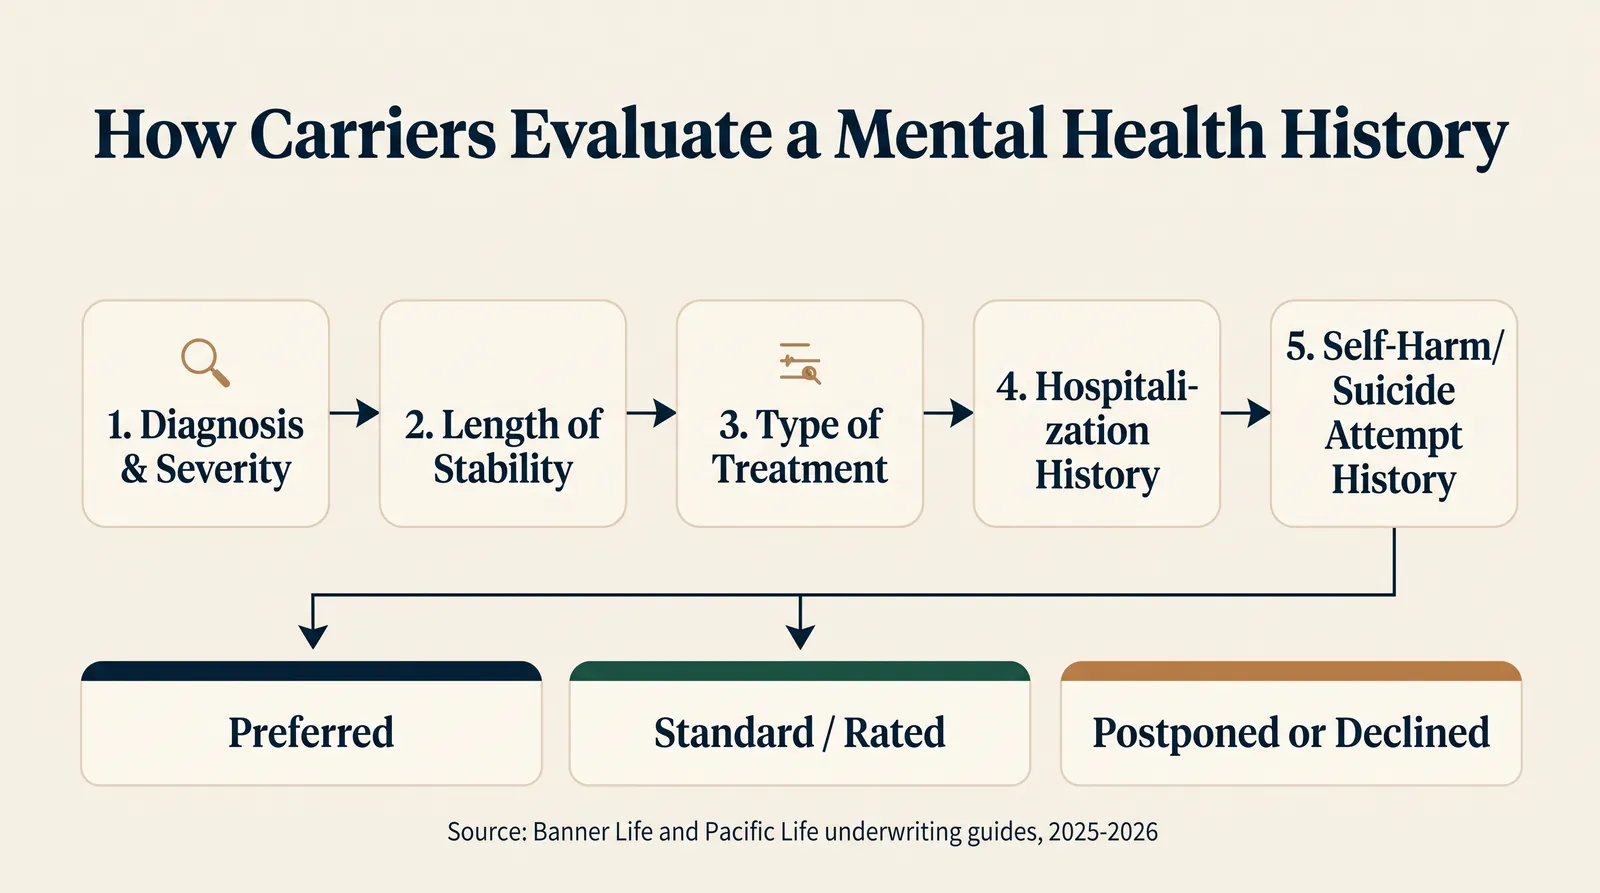
Banner Life’s Field Guide for Life Insurance Underwriting (March 2026) lists anxiety, bipolar, and depression together under “Medical best classes” and states that ratings vary based on: length of stability, severity, type of treatment, employment, any hospitalization history, and any suicide attempt or self-harm history. For each condition specifically, the guide states:
- Anxiety: Preferred Plus (the carrier’s top non-tobacco class) is possible if mild and well controlled on a single medication.
- Depression: Preferred Plus is possible for a single episode lasting less than a year with no current medication. Preferred (the next tier down) is possible for mild depression well controlled on one medication.
- Bipolar disorder: Standard Plus may be possible if mild, well-followed, compliant with treatment, and stable for at least five years.
Pacific Life’s Underwriting Guide (PLF4249-01, dated November 2025) groups the same territory as “Anxiety, Mood, Stress, and Adjustment Disorders” and states that an Attending Physician Statement is typically required for schizophrenia, bipolar disorder, PTSD, eating disorders, an attempted suicide, or a treatment or medication change within the last six months, but is not automatically required otherwise. The guide states plainly: “Preferred classes may be available depending on diagnosis, severity, and recovery,” with outcomes otherwise varying “by severity and control.”
| Scenario | Banner Life family of companies | Pacific Life |
|---|---|---|
| Mild anxiety, well controlled, one medication | Preferred Plus possible; APS typically not required | Preferred classes may be available depending on severity and control |
| One depressive episode, under 1 year, no current medication | Preferred Plus possible | Varies by severity and control; APS usually required |
| Bipolar disorder, stable 5+ years, treatment-compliant | Standard Plus may be possible | APS required; outcome varies by diagnosis, severity, recovery |
| Bipolar disorder, diagnosed within the last year | Listed as a decline/postpone trigger | Likely declined for hospitalization within the last year |
| Suicide attempt, single, within the last 1-2 years | Postpone (decline factor rises at 10 years for some contexts) | Listed as uninsurable within 1-2 years |
| Schizophrenia, 1+ year of documented stability | Possible consideration with treatment compliance, minimal symptoms, employed | APS required; outcome varies by diagnosis and recovery |
Sources: Banner Life family of companies (Banner Life Insurance Company and William Penn Life Insurance Company of New York), Field Guide for Life Insurance Underwriting, March 2026; Pacific Life Insurance Company, Underwriting Guide: Confidence for Generations (PLF4249-01), November 2025. Both guides state that individual underwriting decisions depend on the full case and may differ from these best-case scenarios. Every carrier sets its own guidelines; these two are shown as examples, not the full market.
Two things stand out from putting these side by side. First, both carriers converge on the same handful of factors that actually move the needle: how recent the diagnosis or last episode was, whether treatment is working, and whether there’s been hospitalization or a self-harm history. Second, the two carriers don’t always land in the same place on the same scenario, which is exactly why shopping matters when a health history is part of the picture. A file that gets a cautious answer from one carrier can get a meaningfully better one from another, because each company sets its own underwriting philosophy and risk appetite.
These are illustrative examples, not a promise
The table above reflects two carriers' published guidelines as of the dates shown, describing best-case outcomes under specific, favorable conditions. Underwriting decisions are made case by case, guidelines change, and other carriers set their own rules that may differ from either example here. Nothing here is a quote, an approval, or a guarantee for any individual applicant.
A worked, hypothetical example
Take a hypothetical, illustrative case: a 34-year-old South Dakota resident was diagnosed with mild depression two years ago after a difficult stretch at work, started a single antidepressant medication at that time, has taken it consistently since, has not been hospitalized, and has no history of self-harm. Nothing about their day-to-day life has changed because of it; they work full time and see their doctor for regular follow-ups.
Under Banner Life’s published guide, a well-controlled case on a single medication can reach the Preferred class, the second-highest non-tobacco tier, not a decline, and not the bottom of the scale. Under Pacific Life’s guide, this scenario likely does not sit on the list of conditions requiring an Attending Physician Statement at all, since ongoing single-medication, well-controlled anxiety is one of the few named exceptions, though depression specifically may still call for medical records depending on the case. This is a hypothetical example built to show how the mechanics work, not a benefit estimate or approval for any real applicant; every case is evaluated on its own facts.
Compare that to the version of this story that keeps people from ever applying: I take medication for depression, so I assume I’m stuck with the most expensive option available, or no coverage at all. Based on what these two carriers actually publish, that assumption is very likely wrong for a well-controlled, single-episode case like the one above.
Assuming a mental health history means "no" before applying
- Treats any diagnosis, medication, or past hospitalization as automatically disqualifying
- Never checks what a specific, current carrier's guidelines actually say about the applicant's specific history
- Either skips applying for coverage entirely or defaults to one option without comparing
Common outcomeCoverage never gets sized or bought, based on an assumption that isn't checked
Laying out the specifics and comparing carriers
- Gathers the diagnosis, timeline, treatment, and any hospitalization or self-harm history up front
- Compares how more than one carrier's guidelines treat that specific history, since guidelines vary
- Applies with a carrier whose published criteria actually fit the applicant's situation
Common outcomeAn actual underwriting decision, not a guess, and a comparison across carriers instead of one
What it costs to guess wrong
The real cost here isn’t a specific dollar figure; it’s what happens when the assumption of “I’ll be declined” goes unchecked. Given how common a mental health history is, at 18.2% of South Dakota adults reporting an ever-diagnosed depressive disorder per the 2024 BRFSS data cited above, that’s not a small slice of the population making this same assumption. Two outcomes tend to follow, and both are avoidable:
- Going without coverage entirely, because applying feels pointless. If something happens to that person, the mortgage, the income replacement, the final expenses, none of it gets covered, not because they were actually uninsurable, but because they never found out.
- Applying with only one carrier, usually whichever company an ad or a search result surfaced first, and treating whatever answer comes back as the final word on “am I insurable,” when a different carrier’s published guidelines, like the comparison table above shows, might land somewhere else entirely.
Both of those trace back to the same root problem: treating an assumption as a fact instead of checking it against what carriers actually publish.
Don't confuse this with no-exam or guaranteed-issue coverage
No-medical-exam and guaranteed-issue life insurance are real product categories that exist for people whose health history makes traditional underwriting harder. They're worth knowing about as a category. But jumping straight to one of those, without first checking what a fully underwritten policy's actual outcome would be for a specific, well-controlled history, can mean paying for a smaller amount of coverage than a person may have qualified for through the standard process. Compare both paths before assuming you need the second one.
How to work through this yourself before you apply
Here’s the method, laid out step by step, no gatekeeping:
- Write down the specifics of your history. The exact diagnosis or diagnoses, when each started, current medication and dosage, how long you’ve been on it, any hospitalization (dates and reasons), and any history of self-harm or suicide attempts. Underwriters ask for exactly this level of detail, so having it ready before you apply speeds up the process and reduces back-and-forth.
- Note your stability timeline. Both carriers’ guides above weight how long a condition has been stable, treatment-compliant, and symptom-controlled. A diagnosis from six years ago that’s been fully managed since reads very differently to an underwriter than one from six months ago.
- Understand the narrow list of things that actually trigger a decline or postponement. Based on the two guides above, that’s mainly: a very recent diagnosis of bipolar disorder or schizophrenia, a suicide attempt within roughly the last one to two years, current hospitalization, or a medication change within the last six months. Outside those specific triggers, most histories are rated, not declined, meaning they get an offer at some class, even if it isn’t the very top one.
- Answer every application question honestly and completely. Life insurance applications typically carry a contestability period, commonly two years, during which an insurer can investigate a claim and deny it for a material misstatement. Leaving something out to improve your odds up front creates real risk for your beneficiaries later.
- Compare more than one carrier before drawing a conclusion. The side-by-side table above shows two carriers can land in different places on the same scenario. If one company’s answer doesn’t feel right, that isn’t necessarily the final answer, it may just be that company’s particular risk appetite for your specific history.
How we help
We’re an independent agency, which means we’re not tied to one carrier’s risk appetite. When a mental health history is part of someone’s picture, that independence is exactly the point: instead of taking one company’s guidelines as the final word, we can look at how different carriers actually treat that specific history and compare the real options. We start with the specifics, the diagnosis, the timeline, the treatment, not a guess, and work from there. Compare My Options.
What you get
An actual underwriting answer instead of an assumption you never checked. A comparison across carriers instead of a single company’s guidelines standing in for “what’s possible.” And, if coverage makes sense once you have real numbers in front of you, a policy sized to your actual situation rather than whatever felt safest to guess at.
A mental health diagnosis on your chart is not the same thing as a decline letter in your mailbox. The two carriers whose own guides we reviewed here would tell you the same thing: it depends on the specifics, and most specifics don't end in "no."
Mike MooreRelated reading
If a health condition more broadly is the concern, see our guide to getting life insurance after a health condition. If you’re specifically weighing the exam-free path, see underwritten vs. no-exam life insurance and how no-medical-exam life insurance actually works. And if you’re comparing this against another specific health condition, see our guides on life insurance with diabetes and life insurance after cancer.
Not sure this is the only condition in your file?
Weighing the no-exam route?
Read about no-medical-exam life insurance as a category before deciding.
Not ready to talk to anyone yet?
Read how it works first and come back when you are.
Frequently asked questions
Does having anxiety or depression automatically disqualify you from life insurance?
No. Carrier underwriting field guides published in late 2025 and early 2026 show that mild, well-controlled anxiety or a single past episode of depression can qualify for a carrier’s top rate classes. Underwriters look at severity, how long the condition has been stable, the type of treatment, and any hospitalization or self-harm history, not the diagnosis alone, according to field guides published by Banner Life family of companies (March 2026) and Pacific Life Insurance Company (November 2025).
What mental health conditions are hardest to get approved for life insurance?
Based on two carriers’ published underwriting field guides, the conditions that most often trigger a decline or a postponed decision are: a bipolar diagnosis within the last year, a suicide attempt within the last one to two years, current hospitalization or a treatment/medication change within the last six months, and schizophrenia (which may be reconsidered after about a year of documented stability). Every carrier sets its own guidelines, and these are illustrative examples from two carriers, not a universal rule or a promise about what any individual applicant will be offered.
Will I have to see a doctor or get medical records pulled if I disclose a mental health condition?
Often, yes. Pacific Life’s underwriting guide lists an Attending Physician Statement (APS), meaning your medical records, as typically required for schizophrenia, bipolar disorder, PTSD, eating disorders, a past suicide attempt, or a recent treatment or medication change. Banner Life’s guide makes a narrow exception: an APS usually is not required for mild anxiety that’s well controlled on a single medication. Requirements vary by carrier, coverage amount, and your age.
Does taking medication for depression or anxiety hurt my chances?
Not by itself. Federal survey data shows medication use for depression is common: 11.4% of U.S. adults reported taking prescription medication for depression in 2023, according to the CDC’s National Center for Health Statistics. Carrier guides treat medication as one factor among several, alongside how long you’ve been stable, the severity of the original diagnosis, and whether treatment is working, not as an automatic red flag.
How common is a depression or anxiety diagnosis, really?
Common. An estimated 13.1% of U.S. adolescents and adults age 12 and older had depression during a given two-week period between August 2021 and August 2023, according to the CDC’s National Center for Health Statistics, up from 8.2% in 2013-2014. In South Dakota specifically, 18.2% of adults reported ever being diagnosed with a depressive disorder as of 2024, per an analysis of CDC Behavioral Risk Factor Surveillance System data by America’s Health Rankings.
Should I lie or leave out my mental health history on a life insurance application?
No. Life insurance applications are signed statements, and most policies carry a contestability period, typically two years, during which an insurer can investigate and deny a claim based on a material misstatement on the application. Answer every health question honestly. If your history is more complicated than a single form allows, that is exactly the kind of situation an independent agent can help you present clearly to the right carrier.
What should I actually do if I’m worried a mental health history will get me declined?
Gather the specifics before you apply: your diagnosis, when it started, your current treatment and medication, whether you’ve been hospitalized or had a self-harm episode, and how long you’ve been stable. Then compare how different carriers treat that specific history, since guidelines vary company to company, rather than assuming the worst from one company’s rules or a single past experience.
Sources
- CDC/National Center for Health Statistics — Data Brief No. 527, Depression Prevalence in Adolescents and Adults: United States, August 2021-August 2023 — published April 2025; 13.1% overall 2-week depression prevalence (up from 8.2% in 2013-2014); age breakdowns (20-39: 16.6%, 40-59: 10.8%, 60+: 8.7%); accessed August 2026
- CDC/National Center for Health Statistics — Data Brief No. 528, prescription medication use for depression — published April 2025, National Health Interview Survey 2023 data; 11.4% of U.S. adults took medication for depression (women 15.3%, men 7.4%); accessed August 2026
- National Institute of Mental Health — Major Depression statistics — 8.3% of U.S. adults (21.0 million) had a major depressive episode in the past year, 5.7% (14.5 million) with severe impairment, 61.0% received treatment; 2021 National Survey on Drug Use and Health data; accessed August 2026
- America’s Health Rankings — Depression, South Dakota — analysis of CDC Behavioral Risk Factor Surveillance System data; 18.2% of South Dakota adults ever diagnosed with a depressive disorder vs. 22.0% U.S. average, 2024 data; accessed August 2026
- Banner Life family of companies — Field Guide for Life Insurance Underwriting — March 2026 edition; anxiety, bipolar, and depression best-class guidelines; declines and postpones list; accessed August 2026
- Pacific Life Insurance Company — Underwriting Guide: Confidence for Generations (PLF4249-01) — November 2025 edition; Anxiety, Mood, Stress, and Adjustment Disorders underwriting criteria; uninsurable conditions and timelines; accessed August 2026
Related reading: getting life insurance after a health condition, underwritten vs. no-exam life insurance, no-medical-exam life insurance in South Dakota, life insurance with diabetes, and life insurance after cancer.
Before you act on any of this
This article is general education, not insurance, legal, financial, medical, or tax advice, and it is not an underwriting decision or a promise of coverage for any individual. Carrier guidelines shown here are illustrative examples current as of the dates listed and are subject to change; other carriers set different rules. Product availability, features, and rates vary by carrier and are subject to underwriting. No coverage exists until a policy is issued and in force. Any guarantees are subject to the claims-paying ability of the issuing insurer. Please review actual policy documents and speak with a licensed agent about your own situation.
The real answer is worth more than the assumption
Most people who assume a mental health history closes the door on life insurance have never actually checked, because the fear of a “no” feels worse than not asking. What two carriers’ own published underwriting guides show is a lot more specific, and a lot less bleak, than that fear: severity, stability, treatment, and history, not the diagnosis alone. You can write down your own specifics this week, the diagnosis, the timeline, the treatment, and see how they line up against what’s actually written above. That comparison is worth more than another year of guessing.
Want an actual answer instead of a guess?
We'll walk through your specific history and compare carrier options sized to what's actually in your file, not an assumption about it.